How the Anion Gap Measures
The anion gap is a calculated value that assists clinicians interpret an electrolyte panel and recognize hidden drivers of acidemia. It shows the difference between measured cations and measured anions in serum chemistry, mainly using serum sodium, serum chloride, and serum bicarbonate. Because the body maintains electrical neutrality through buffer systems and other charged particles, the gap offers clues about unmeasured anions that may be present in acid-base disorders.
In practical terms, the anion gap acts as a diagnostic tool for sorting through causes of metabolic acidosis. A widened gap often suggests accumulation of acids such as organic acids or other toxins, while a normal gap can point toward bicarbonate loss or impaired acid handling. This makes the anion gap important in the overall diagnostic approach to systemic illness and metabolic derangement.
Although the number is simple, the meaning is not. The result must be interpreted alongside laboratory values, symptoms, and acid-base status. A calculator can quickly produce a number, but good clinical interpretation depends on whether the patient has true acidemia, whether there is a respiratory component, and whether albumin is altering the expected reference range.
How to Use an Anion Gap Calculator
An anion gap calculator is most useful when you already have a new basic metabolic panel or comparable lab set. The calculator usually asks for serum sodium, serum chloride, and serum bicarbonate. Some versions also include albumin so they can report an albumin correction and provide a more precise corrected value.
To use the tool, enter the measured values exactly as reported. The calculator then calculates the difference between major measured ions and displays whether the result falls within the expected range. If albumin is low, the calculator may correct the output to account for the lower concentration of negatively charged proteins. That correction matters because hypoalbuminemia can make a clinically important gap look deceptively normal.
The calculator is not a diagnosis by itself. It is a quick way to systematize data from the electrolyte panel and aid decision-making. When the output suggests a widened gap, the next step is to examine whether the patient has metabolic acidosis on blood gas testing and whether the pattern fits a known cause such as lactic acidosis, ketoacidosis, renal failure, or toxic alcohols.
In a high-volume clinical setting, the calculator can also help standardize interpretation across different providers. It turns raw numbers into a structured interpretation guide that supports quicker recognition of dangerous acid-base problems.
Anion Gap Calculation & Step-by-Step Calculation
The standard anion gap formula is based on a basic calculation using reported electrolytes. In its typical form, the calculation is:
anion gap = sodium minus chloride minus bicarbonate
Some references use slightly different formulas, such as sodium minus the sum of chloride and bicarbonate written in a different form, but the idea is the same. The calculation approximates the amount of unmeasured anions in the plasma. Because the body contains many charged particles beyond the routine lab panel, the gap represents an anion deficit in the measured list rather than an true missing ion.
Here is the step-by-step reasoning:
- Begin with serum sodium, which is the dominant measured cation. Subtract serum chloride, the major measured anion. Subtract serum bicarbonate, another measured anion related to acid-base balance. Review the remaining value as the estimated anion gap.
If albumin correction is needed, the result is adjusted upward when albumin is low. This may help reveal hidden acid accumulation that might otherwise be masked. The corrected result is often more informative in patients with chronic illness or critical illness, where protein levels can be significantly reduced.
The biggest benefit of the formula is simplicity, but its meaning depends on context. A minor change in bicarbonate can indicate significant acid-base disturbance, while a normal number does not automatically exclude serious disease.
Normal Anion Gap versus Elevated Anion Gap Acidosis
A key one of the most useful applications of the anion gap is separating between normal anion gap metabolic acidosis and high anion gap metabolic acidosis. Each are varieties of metabolic acidosis, but they vary in mechanism.
In normal anion gap metabolic acidosis, bicarbonate is reduced or neutralized without a significant rise in unmeasured acids. The chloride level often goes up to maintain electrical balance, so the gap remains within the expected normal range. Frequent clinical scenarios include gastrointestinal bicarbonate loss and certain renal tubular problems, though the exact cause must be evaluated one case at a time.
In high anion gap metabolic acidosis, the body accumulates acids that are not directly measured by routine chemistry testing. These acids deplete bicarbonate and leave behind negatively charged substances, widening the gap. This pattern is often seen with lactic acidosis, ketoacidosis, renal failure, and ingestion of toxic alcohols.
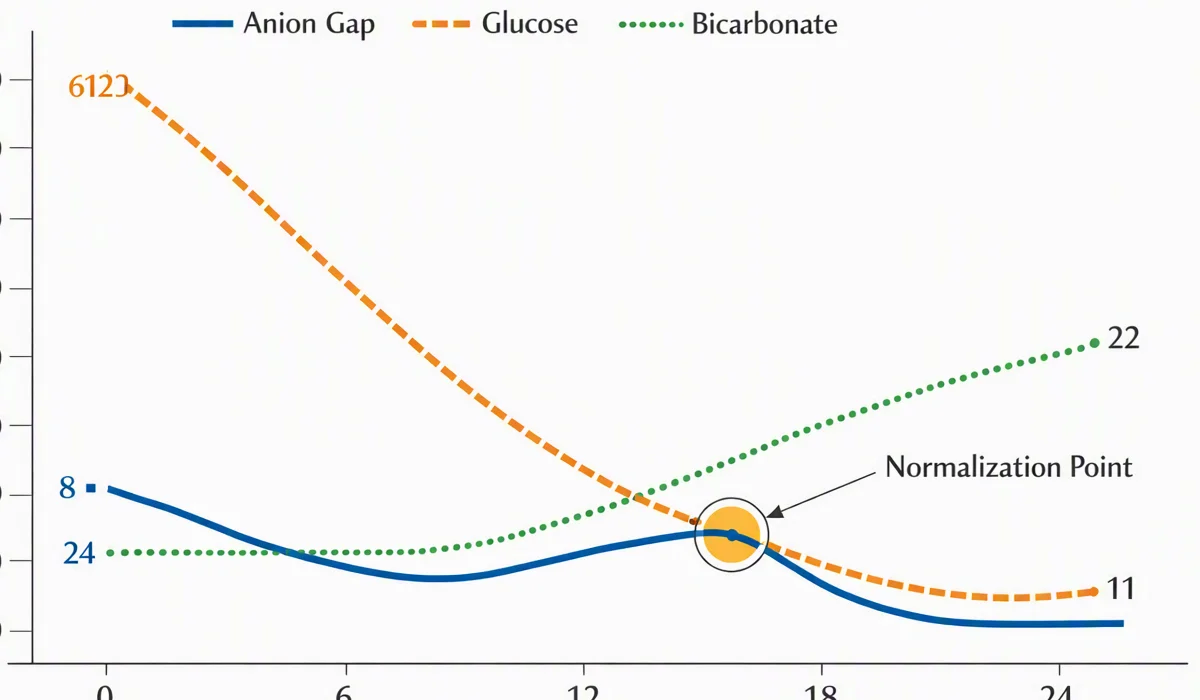
Recognizing the difference helps refine the diagnostic evaluation. These patterns can present with low bicarbonate and a low pH, but the gap helps show whether the issue is primarily bicarbonate loss or accumulation of unmeasured acid. This is why the anion gap remains important to evaluation of acid-base disorders and systemic acidosis.
Albumin Adjusted Anion Gap
Albumin acts as one of the major unmeasured anions in blood. When albumin decreases, the anion gap can decrease even if significant acids are present. This is why hypoalbuminemia can result in underrecognition of an elevated gap unless an albumin correction is applied.
The corrected anion gap is especially useful important in critical illness, where albumin levels are often low because of inflammation, dilution, or poor nutrition. In these settings, a seemingly normal uncorrected gap may hide important acid accumulation. The correction helps restore the result closer to its expected physiologic meaning.
Why should this be considered? Because albumin contributes a substantial portion of the body’s negative charge. When it drops, the measured gap narrows even though the underlying cause of acidemia may not improve. A corrected value gives a better estimate of the true acid burden and improves clinical interpretation.
In practical use, always consider the albumin level before dismissing a borderline result. If the patient has hypoalbuminemia, the corrected gap may reclassify the case from normal to high and modify the differential diagnosis substantially.
Typical Causes of Elevated Anion Gap Acidemia
If the calculator reveals a higher gap, the next step is to identify the cause of the acidemia. Several well-known conditions produce high anion gap metabolic acidosis.
- Lactic acidosis — Frequently seen with hypoperfusion, sepsis, hypoxemia, or severe metabolic stress. Excess lactate reflects impaired oxygen delivery or altered metabolism. Ketoacidosis — Seen when ketone production rises, such as in diabetic crises, prolonged fasting, or alcohol-related states. Ketones are acidic and worsen the gap. Renal failure — Reduced kidney function limits acid excretion and allows acidic solutes to accumulate over time. Toxic alcohols — Ingestions such as methanol or ethylene glycol can generate acidic metabolites and produce severe metabolic derangement.
Other causes may also be considered depending on the case, but these four are among the most common and clinically significant. A widened gap reflects the presence of unmeasured acids, so the task is to ask what acids are likely present and whether the clinical picture fits.
That is why the calculator is best used as part of a more complete workup rather than as a standalone result. The answer should be integrated with history, examination, and complementary labs. In many cases, the anion gap points the clinician toward targeted testing for lactate, ketones, kidney function, or toxic exposures.
How to Read Values in Medical Context
The anion gap turns far more informative when interpreted alongside pH and arterial blood gas readings. A patient may have an increased gap on chemistry testing, but without acidemia on blood gas, the picture may be blended or partially compensated. Likewise, a decreased pH with a normal gap can still represent significant disease.
Breathing response matters too. Respiratory compensation is the body’s attempt to lower carbon dioxide and reduce the fall in pH during metabolic acidosis. The relationship between pH, bicarbonate, and carbon dioxide helps determine whether compensation is adequate or whether another process is present.
That is where the delta gap becomes helpful. Delta gap reasoning compares the rise in anion gap with the fall in bicarbonate to identify mixed acid-base disorders. If the gap has increased more than bicarbonate has fallen, there may be an additional metabolic alkalosis. If bicarbonate is lower than expected for the degree of gap elevation, a concurrent normal-gap acidosis may also be present.
This layered analysis is especially helpful in complex illness. A patient with infection, kidney dysfunction, and vomiting may have multiple overlapping acid-base disorders. In those situations, the calculator provides a starting point, but the final answer depends on the overall pattern of acid-base disorders.
Interpretation should always be practical: ask whether the patient has a clinically significant metabolic acidosis, whether the respiratory system is compensating appropriately, and whether the gap matches the suspected cause. The calculator helps arrange the numbers, but the diagnosis comes from clinical judgment.
Challenges and Constraints of Anion Gap Calculation
As with every lab-based tool, the anion gap has constraints. One common issue is lab error, which can alter the numbers and yield a misleading result. If the value does not fit the clinical picture, retest and review specimen quality before drawing conclusions.
Another major limitation is the influence of albumin. Without correction, a low albumin level can mask a widened gap. That means a patient with true acid accumulation may look like they have a normal result if the correction is not considered.
Paraproteinemia is an additional significant concern. Abnormal proteins can change the measured chemistry and change the expected gap. In some cases, these proteins may behave as unexpected charged species and obscure the usual pattern.
It is also important to remember that the gap estimates unmeasured anions, not a specific disease. A high number tells you that something acidic is accumulating, but it does not determine the cause. The clinician must still evaluate for lactate, ketones, renal dysfunction, and toxins, among other possibilities.
Finally, the normal range is not universal. Different laboratories and methods may use slightly different ranges, so always interpret the result using the local reference range. Small differences in assay design and reporting can affect what is considered normal.
FAQ About Anion Gap and Acidemia Evaluation
What is the anion gap calculator used for?
The anion gap calculator is used to estimate the gap from routine lab values and support evaluation of metabolic acidosis and acidemia. It helps clinicians identify whether the pattern suggests a normal gap or a widened gap and provides a starting point for acid-base interpretation.
What is a normal anion gap range?
The normal range varies by laboratory method, so the result should be compared with the local reference range. In general, a value that falls within the expected range suggests normal anion gap physiology, but clinical context still matters.
Why is it corrected the anion gap for albumin?
You adjust for albumin because low albumin decreases the measured gap and can hide a true elevation. Albumin correction enhances detection of acid accumulation, especially in Check out the post right here patients with hypoalbuminemia or critical illness.
What can cause a high anion gap in acidemia?
Common causes of a high gap include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. These conditions add to unmeasured anions and often produce high anion gap metabolic acidosis.
Can a normal anion gap still occur with metabolic acidosis?
Yes, it can. Normal anion gap metabolic acidosis is a recognized form of metabolic acidosis and can occur when bicarbonate is excreted or replaced by chloride. The acid-base picture must be evaluated with pH, arterial blood gas, and the broader clinical context.